
How to Manage Severe Chemotherapy Side Effects Without Stopping Treatment: An Oncology-Specific 7-Step Guide

Introduction
You are in the middle of a chemotherapy cycle, and the body you live in feels like a hostile landscape. The nausea chains you to the bathroom, a corner of your mouth tears open, and a thermometer's reading on a Tuesday evening suddenly becomes the most terrifying number in your life. When side effects feel this brutal, the thought of the next infusion is unbearable.
But stopping the protocol is not the same as managing the crisis. The American Cancer Society frames this aggressively: the moment you stop communicating, your chance of staying on schedule collapses. The worksheet they provide drills a single point: severe side effects don't automatically mean the treatment is failing; they mean the management plan needs an immediate escalation that you and your care team run together. About 15 to 20% of leukemia patients face relapse after remission, and while some of those relapses are biologically driven, a pattern emerges when patients abandon a treatment path because the support scaffolding wasn't in place. The National Cancer Institute's 'Chemotherapy and You' guide treats patient self-monitoring as a non-negotiable daily function.
This article gives you that scaffolding. It is a home-clinic partnership model: seven concrete steps that transform a mess of terrifying symptoms into a tracked, treatable set of signals. Every step pulls from oncology supportive care protocols, the NCCN antiemesis guidelines, and the practical economics of navigating this in India. You'll learn the threshold where 'severe' tips into 'emergency,' when exactly you pick up the phone, and how infrastructure like home-based chemotherapy can keep a protocol alive when your body is too exhausted to travel.
Key Takeaways
What you act on this week is what keeps your treatment on schedule. The line between a severe side effect managed at home and a life-threatening neutropenic crisis is policed by these core protocols:
Fever is a single-number emergency: a temperature of 100.5°F (38°C) or a sustained 38.0°C for more than one hour is a neutropenic fever threshold requiring an immediate call to your oncologist, not a next-morning check-in.
Antiemetics work only when taken before symptoms start: the NCCN antiemesis guidelines structure drugs like aprepitant, dexamethasone, and palonosetron into a pre-emptive 'round the clock' protocol, not a reactive one; you cannot catch up to nausea once it's established.
Severity-tier the low blood counts: low white blood cells (neutropenia) require growth factor injections like filgrastim (Neupogen); low red blood cells (anemia) produce breathlessness and demand immediate lab correlation; low platelets (thrombocytopenia) show up as unexplained bruises or bleeding gums and restrict activity to prevent intracranial hemorrhage.
Diarrhea is quantified, not guessed: the tracking sheet defines moderate diarrhea as 4 to 6 more stools than usual, and severe as 7 or more stools plus weakness; crossing into severe territory without intervention risks pre-renal failure from dehydration.
Treatment abandonment in India has a financial fix: Ayushman Bharat PM-JAY provides ₹5 lakh coverage at empanelled hospitals, generic cancer medications cost up to 80% less than branded equivalents, and clinical trial participation can save ₹5 to 25 lakhs; your center's financial counselors verify this eligibility.
Step 1: Implement a Daily Symptom-Tracking System to Catch Severe Reactions Early
A delayed escalation can permanently derail a chemotherapy schedule. Your clinic already knows this: severe immunosuppressive regimens often require admitting the patient for inpatient monitoring. When you are at home between cycles, you become your own surveillance unit. The American Cancer Society's Chemotherapy Side Effects Worksheet breaks this down into a daily log: temperature taken at the same time daily, number of bowel movements compared to your pre-chemo baseline, pain level on a 1-to-10 scale anchored to function, and whether every mouthful of food or water made it through. A BP monitoring machine checks blood pressure at home, because orthostatic dizziness can flag the onset of severe dehydration or anemia hours before lab values reflect it.
This worksheet is the structured input your oncologist uses to make a dose-modification decision. When you present your team with data showing you have had 7 or more stools than usual plus dizziness, that 'severe' classification bypasses subjective description and triggers a protocol. A fever of 100.5°F logged in a worksheet entry works faster than panic: you know exactly when you crossed the emergency threshold beneath which oral antibiotics cover the gap, and above which you need immediate IV antibiotics and G-CSF. Print the worksheet, keep it next to the thermometer, and fill it out as your first medical intervention of the day.
Step 2: Master Proactive Antiemetic Protocols to Prevent Nausea and Vomiting
The single fact that rearranges chemotherapy nausea management is that antiemetics are a preventive protocol, not a rescue medication. The moment you feel nauseous, you have already failed the window for the most effective intervention. The NCI's chemotherapy guide states this baldly: medications must be taken before symptoms begin.
Acute nausea kicks in within the first 24 hours after infusion, while delayed nausea emerges days two to five and is the more psychologically destructive variant because it breaks you down when you think the worst is over. Pharmacological management of CINV includes 5-HT3 receptor antagonists, NK1 receptor antagonists, and corticosteroids, combined into what an oncologist tailors to your regimen's emetogenicity risk level. A common anti-vomiting triple that illustrates the principle is aprepitant, dexamethasone, and palonosetron, started hours before the infusion and continued on a fixed schedule for days afterward.
You do not self-adjust this schedule, and you don't try to 'tough out' a wave of nausea before taking another pill. Inadequate control of nausea and vomiting should prompt contact with the oncology center that administered the chemotherapy, because continuing to vomit without pharmacological intervention causes electrolyte derangement and rapid malnutrition. There is no additional benefit to taking medications for chemotherapy-induced vomiting after the prescribed duration, but stopping them early leaves you vulnerable to the delayed emesis window. For breakthroughs that cannot be controlled orally, the page notes that refractory breakthrough vomiting may need IV injections and supportive care like saline infusion, which is exactly the kind of home-clinic intervention that a daycare chemotherapy suite is built to handle. Non-pharmacologic interventions like acupressure, acupuncture, and ginger have shown efficacy in reducing CINV severity for some patients, but never substitute these for the main protocol; they ride alongside it.
Step 3: Manage Fatigue, Pain, and Low Blood Counts with Severity-Based Interventions
Cancer-related fatigue, mild pain, and hematologic toxicity require a tiered approach where you match the severity to a specific action set. Follow this sequence:
Conserve energy for necessary activity only: chemotherapy fatigue is a marrow-suppression and metabolic reality. Rest, short walks, and high-calorie foods are your baseline interventions. If fatigue is not relieved by rest, or causes trouble walking or a fall, that is a severe threshold the worksheet flags for an immediate team call.
Use prescribed analgesics, not NSAIDs, for mild pain: the page warns that chronic NSAID use can result in kidney injury, and some chemotherapy agents themselves are nephrotoxic. Avoid compounding the damage; use the acetaminophen or opioid-based analgesic your oncologist prescribes. Pain that prevents eating or drinking is graded as severe and requires clinic contact the same day.
Track the distinct symptoms of low white cells, red cells, and platelets: white cell depletion (neutropenia) typically produces no symptoms until infection sets in, which is why growth factor injections like G-CSF are pre-scheduled. The most common side effect is bone pain that usually starts one to three days after the first dose and goes away once you stop taking it. Low red cells (anemia) produce exertional breathlessness and pallor. Low platelets (thrombocytopenia) produce spontaneous bruising, gum bleeding, and petechiae; this is an immediate report, as platelet transfusions may be necessary to prevent spontaneous intracranial bleeding.
Step 4: Adopt Symptom-Specific Dietary Modifications and Bowel Regimens
Chemotherapy attacks rapidly dividing cells in the entire gastrointestinal epithelium, which means that eating becomes a mechanical and chemical negotiation with a raw mucosal surface. The table below maps three distinct GI side effect clusters to concrete dietary and pharmacologic responses.
Symptom Profile | Dietary & Home Modification | Pharmacologic Support (OTC/Rx) | Escalation Threshold (Call the Team) |
Oral Mucositis (Painful Mouth Sores) | Stick to soft, bland, non-acidic foods: yogurt, custard, khichdi, mashed banana, daal at room temperature. Avoid citrus, tomato, rough grains, and carbonated drinks. Drink 1 to 2 liters of water every day in small sips. Use a non-alcohol mouth rinse (salt-and-soda water) several times daily. | Prescribed topical lidocaine mouthwash before meals. Systemic analgesics if topical is insufficient. | Pain prevents eating or drinking entirely; inability to swallow saliva signals risk of dehydration and possible sepsis through mucosal breach sites. |
Diarrhea (Moderate to Severe Threshold) | Switch to clear liquids and the BRAT-principle foods: banana, plain white rice, applesauce, dry toast. Avoid high-fiber raw vegetables, dairy, and spicy oils. Maintain strict 1 to 2 liters of hydration daily, supplemented with oral rehydration solution (ORS) if stool frequency rises. | Loperamide as directed by the oncology team; do not self-dose if blood or mucus is present. | 4 to 6 more stools than usual is moderate; 7 or more stools than usual plus weakness or dizziness is severe and requires immediate clinic contact. |
Constipation (Opiate- or Vinca-Alkaloid Induced) | Increase hydration, consume warm prune juice, and integrate soluble fiber like isabgol (psyllium husk) only if fluid intake is adequate; insoluble fiber without water creates an obstruction. | Stool softeners (docusate) daily as a preventive base. Stimulant laxatives like bisacodyl and osmotic purgatives like milk of magnesia or polyethylene glycol are used for escalation, not as first-line daily drivers. | Unable to move bowels despite medication for a period matching your team's defined cutoff; severe abdominal pain or bloating with vomiting is an obstruction red flag that requires emergency imaging. |
Step 5: Recognize Fever, Infection, and Mucositis as Medical Emergencies
A fever in a chemotherapy patient is a fundamentally different event from a fever in someone with an intact immune system. One number will become automatic: the chemotherapy side-effects worksheet classifies 100.5°F to 104°F as moderate fever and anything above 104°F as severe. The threshold tightens further to a single reading above 38.3°C, or 38.0°C sustained for more than an hour. At that point you are in neutropenic fever territory. Your absolute neutrophil count has almost certainly fallen below functional levels, your immune surveillance is absent, and every hour you wait opens the door to gram-negative sepsis progressing into septic shock.
Oral mucositis is the less obvious emergency. Chemotherapy strips the mucosal lining of your mouth and gut, leaving raw, bleeding surfaces that bacterial flora can cross directly into the bloodstream. A mouth too painful to drink constitutes a compounding septic risk right now.
The protocol for fever alongside mucositis or a central line is clear: take ciprofloxacin plus amoxicillin and clavulanic acid at adequate doses if you tolerate them. This is a bridge to an immediate clinic or emergency room visit, not a comfort measure. The American Cancer Society advises patients to contact their cancer care team right away for any severe side effect, including inability to eat or drink, severe pain with trouble eating, or a temperature that crosses the threshold.
Step 6: Explore Home-Based and Daycare Chemotherapy Options in India for Continuity
When severe fatigue, painful neuropathy, or repeated infections make the trip to a large hospital building feel impossible, the protocol does not have to stop. India's oncology infrastructure now includes a delivery model designed specifically to solve the transport and exposure problem: daycare and home-based chemotherapy administration.
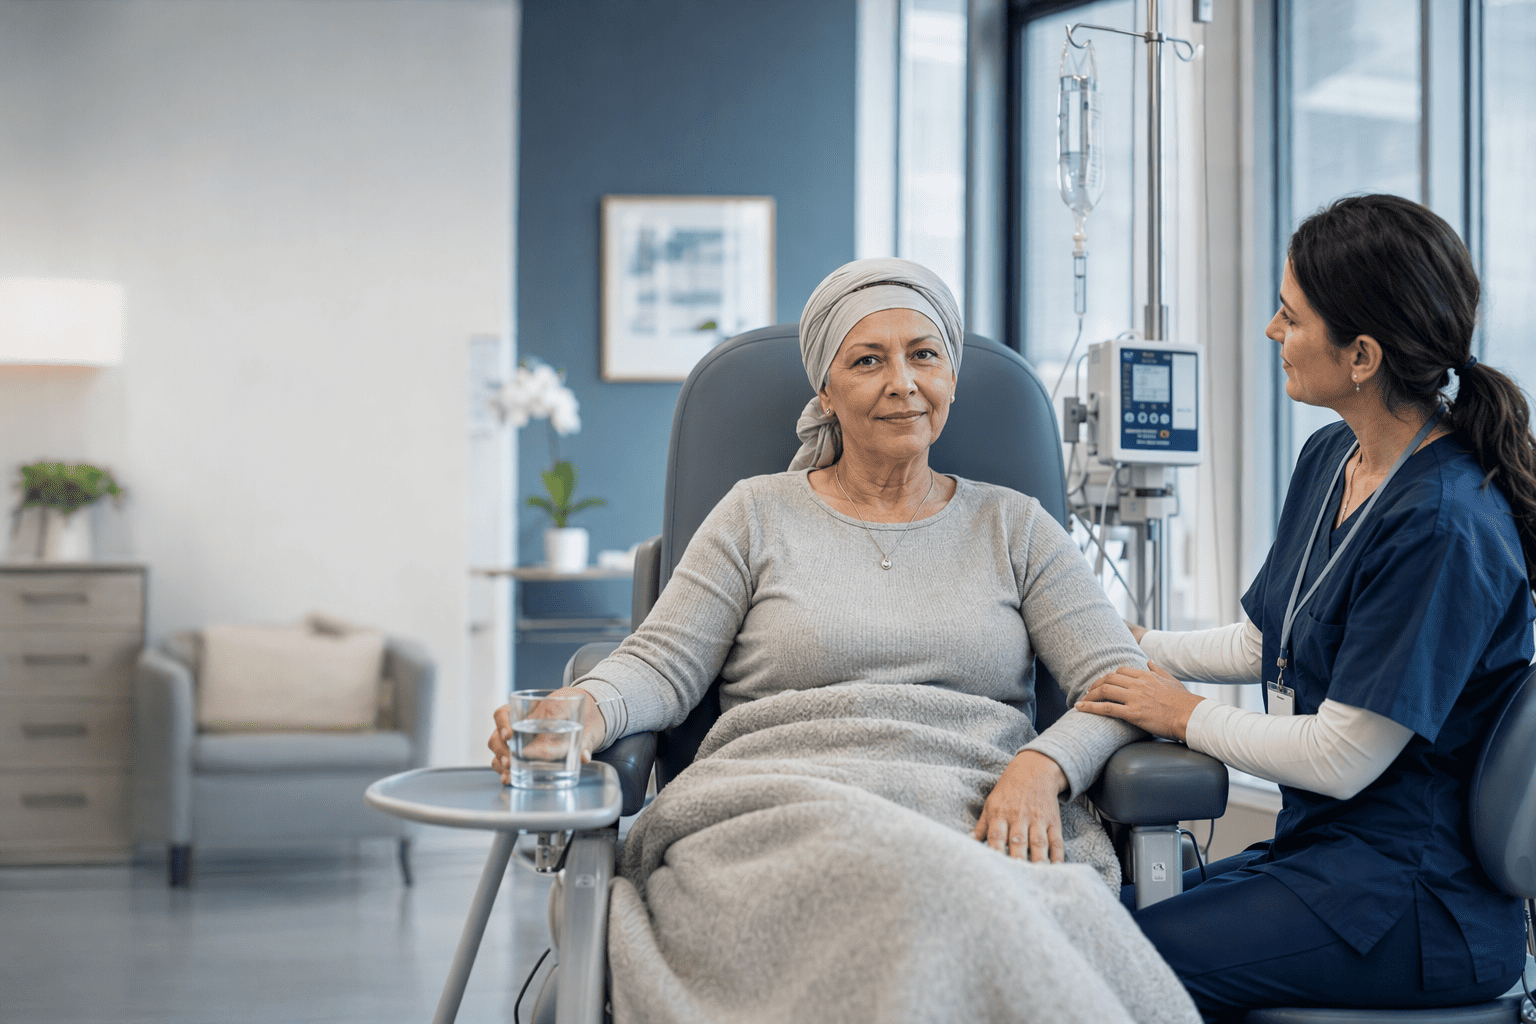
At a dedicated daycare chemotherapy suite, the drug is handled under the same sterility and safety standards as a hospital inpatient unit. The drug must be refrigerated at 2 to 8°C until use, mixed in sterile conditions inside a biological safety cabinet, and given as a controlled IV infusion in a dedicated daycare chemo suite. You sit in a designed clinical environment for the infusion duration, monitored by oncology nurses, but you are not occupying an inpatient bed.
Home-based chemotherapy pushes that model further. It becomes the option that works when a patient is too immunocompromised to safely enter a crowded waiting room or too weak to commute. Dr. Bharat Patodiya offers home-based chemotherapy services through certified nursing teams that administer the pre-tested protocol in your home environment. Home chemotherapy is not suitable for high-dose or investigational regimens that need hospital monitoring, and severe immunosuppressive chemotherapy is often managed by admitting the patient for initial monitoring. But for maintenance cycles where your vitals, labs, and clinical exam are stable, a home-based model preserves the schedule and reduces nosocomial infection exposure.
Fitness for this model is a clinical decision. Your oncologist certifies that the regimen's adverse event profile is predictable, that the infusion does not require a continuous escalation in drugs, and that the home nursing team can be equipped with an emergency kit and a direct telemedicine line. The center provides 24/7 medical supervision through telemedicine channels, which means that a fever spike or infusion reaction at home triggers an immediate clinical video consult rather than an anxious taxi ride.
This model works within India's existing care architecture because the economic and logistical barrier of daily hospital attendance is what drives some patients to skip doses. Removing that barrier keeps the cumulative dose intensity on schedule.
Daycare and home-based chemotherapy fit into India's move toward tiered oncology: you receive dose-dense, immunosuppressive blocks in an intensive care setting, then shift to a lighter, monitored, ambulatory model for the subsequent cycles. This approach cuts inpatient bed charges and daily hospital operational fees from the cost calculation.
Step 7: Navigate Financial Costs and Indian Support Schemes to Avoid Treatment Abandonment
The reported rates of treatment abandonment in India turn on a brutal equation: patients calculate that they can survive the disease longer without treatment than they can survive the financial toxicity of side-effect management. Hidden costs aggregate fast: transport for daily fever checks, nutritional supplements for a raw gut, G-CSF injections at retail pharmacy prices, and lost wages for the caregiver who must become a full-time monitor. Reversing this calculation starts with mapping the three layers of Indian financial support before you self-discontinue.
Layer one is government coverage. Ayushman Bharat PM-JAY provides up to ₹5 lakh coverage at empanelled hospitals, and state health schemes layer on top in several regions. Layer two is the aggressive cost difference between branded and generic supportive drugs: generic cancer medications cost 80% less than branded drugs once they enter the market.
Layer three taps into hospital-specific infrastructure: financial counselors at cancer centers verify government scheme eligibility, coordinate charitable aid applications, and connect patients with clinical trial opportunities. Trial participation can directly reduce the financial load; the page says clinical trial participation can save ₹5 to 25 lakhs in treatment costs while providing access to drugs that are otherwise unavailable.
Dr. Bharat Patodiya's practice operationalizes this multilayered approach by coordinating screening referrals and connecting patients with diagnostic facilities offering transparent pricing, like PET-CT support at ₹5,000 compared with conventional rates of ₹25,000 to ₹40,000. Cost reduction is not separate from medical management; it is the access tool that prevents abandonment.
Conclusion
A protocol runs on a partnership. The oncologist designs the chemotherapy dose, schedule, and growth factor support based on the tumor's biology, but you are the daily operator who lives inside the gap between one cycle and the next. The tools covered in this guide are how you shrink that gap: a worksheet that forces a fever into an emergency response instead of a panicked Google search; an antiemetic protocol taken pre-emptively so you don't cross into a window where adding a drug is too late; a severity-based escalation guide for low blood counts that makes anemia and thrombocytopenia distinct clinical problems with distinct solutions.
The NCI states that chemotherapy works by stopping or slowing the growth of cancer cells, and the American Cancer Society structures its worksheets on the singular principle that side effect management is the main branch of modern oncology. When side effects become severe, the intervention is not despair. It's the escalation protocol in your handout, the daycare or home chemo service you can access within your city, the Ayushman Bharat coverage you activate this week, and the 24/7 line you call when the thermometer reads 100.5°F. There is always something that can be done.
Frequently Asked Questions
What are the most effective strategies to control chemotherapy-induced nausea and vomiting so I can continue my treatment schedule?
The paragraph describes two approaches to managing chemotherapy-induced nausea and vomiting (CINV):
Pharmacological prevention: Take a pre-scheduled triple antiemetic combination like aprepitant, dexamethasone, and palonosetron before symptoms begin; the protocol is preventive and covers both acute and delayed CINV phases.
Non-pharmacologic support and escalation: Ginger or acupressure may help alongside, but inadequate oral control requires immediate IV antiemetics and saline infusion at your oncology center.
How can I manage chemotherapy-related fatigue, pain, and low blood counts without pausing or stopping my infusions?
The paragraph covers three self-management strategies during chemotherapy recovery:
Energy conservation: Restrict activity to key tasks only.
Pain and kidney protection: Use prescribed analgesics instead of NSAIDs to protect your kidneys.
Active blood count tracking: G-CSF injections like filgrastim boost neutrophils; breathlessness or pallor signals anemic drops; unexplained bruises require an immediate platelet-level check; severe fatigue that prevents walking needs a same-day clinical review.
Are there home-based or daycare chemotherapy options available in India that maintain safety while improving quality of life?
The paragraph compares two outpatient chemotherapy delivery models:
Daycare chemotherapy suites: Administer the infusion in a sterile, monitored, outpatient clinical setting.
Home-based chemotherapy: Offered by centers like Dr. Bharat Patodiya’s through certified nursing teams and 24/7 telemedicine supervision, delivering maintenance cycles at home; not suitable for high-dose or investigational regimens that need hospital monitoring.
What financial assistance, generic drug alternatives, or government schemes can reduce the cost of managing severe side effects in India?
The paragraph outlines the four key components of India's multilayered financial support system to prevent treatment abandonment:
Ayushman Bharat PM-JAY: Covers up to ₹5 lakh at empanelled hospitals.
Generic drug pricing: Generic cancer supportive medications cost up to 80% less than branded equivalents.
Hospital financial counselors: Verify scheme eligibility and coordinate charitable aid.
Clinical trial participation: Can save ₹5 to 25 lakhs while providing access to novel agents.
When does a fever or infection become a medical emergency during chemotherapy, and what should I do immediately?
Any single temperature of 100.5°F (38°C) or a sustained 38.0°C for more than one hour is a neutropenic fever emergency. Do not wait overnight. Take prescribed oral antibiotic cover like ciprofloxacin plus amoxicillin-clavulanic acid if your team has pre-authorized it, and proceed to your oncology center’s emergency room immediately for IV antibiotics and G-CSF.
Sources
Cancer Treatment info | Best Oncologist | Dr. Bharat Patodiya - www.drbharatpatodiya.com
Chemotherapy Side Effects Worksheet - www.cancer.org
Chemotherapy and You - www.cancer.gov
[PDF] UMCC 2019.173 Olanzapine for the Prevention of Chemotherapy ... - cdn.clinicaltrials.gov
7 chemotherapy side effects and how to manage them | UT MD Anderson - www.mdanderson.org
New insight into strategies used to develop long-acting G-CSF biologics for neutropenia therapy - PMC - pmc.ncbi.nlm.nih.gov
G-CSF (Granulocyte-Colony Stimulating Factor) Treatment - my.clevelandclinic.org


Comments